Which Medical Plan is Right?
Evaluate Your Needs. Consider your prior health care usage and select plans and options that fit your lifestyle and needs.
- Do you take regular prescription medications?
- Are you anticipating surgery or non-preventive dental care?
- Did you experience a qualifying life event this year?
- Review your current plans to ensure you have the coverage you need.
Review this benefits website to learn about your plan options.
A little bit of planning will help you select the best plans, coverage levels, and financial programs for your unique situation.
Medical Plan Comparison
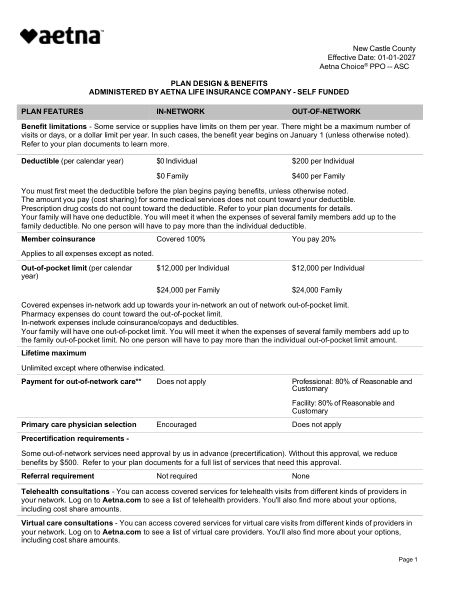
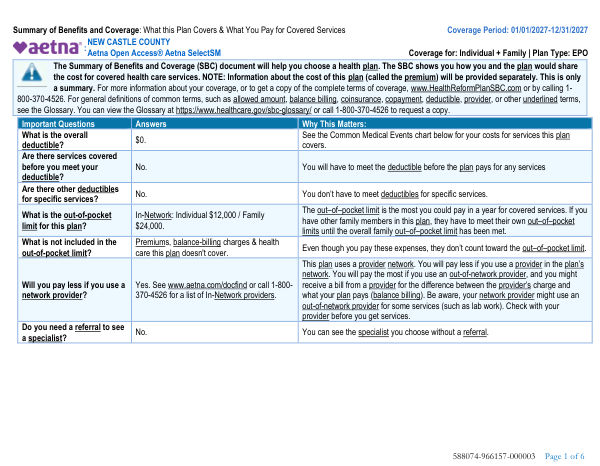
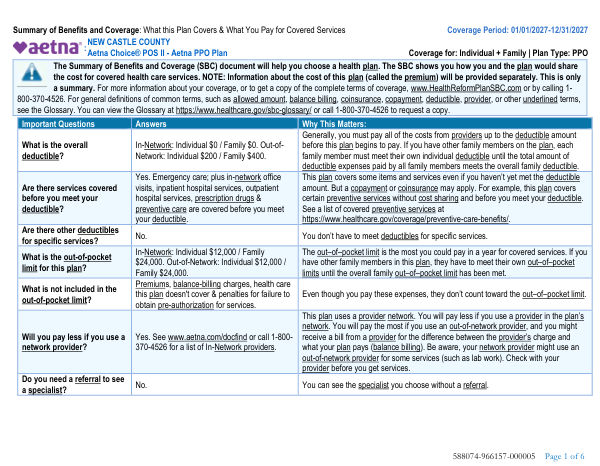
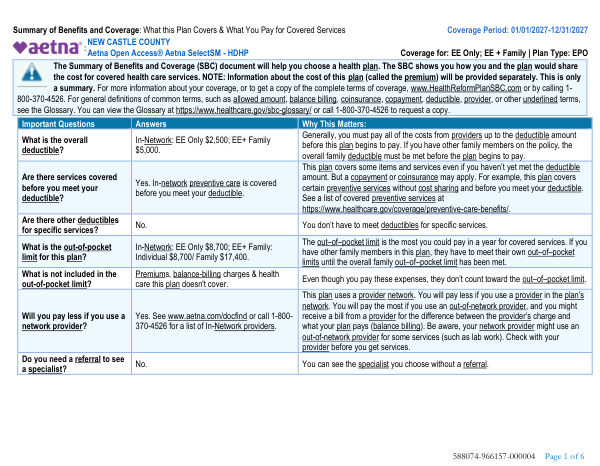
New Castle County will continue to offer medical coverage. The below charts are a brief outline of the plan options for Aetna.
Medical Plan
| FULL-TIME & UNDER 65 | AetnaOpen Access Select | Aetna Aetna PPO |
Aetna Medical QHDHP HSA Compatible |
|||||
|---|---|---|---|---|---|---|---|---|
| Schedule of Benefits | In-Network Benefits | Out-of-Network Benefits | Schedule of Benefits | |||||
| Annual Deductible | ||||||||
| Individual | $0 | $0 | $200 | $2,500 | ||||
| Family | $0 | $0 | $400 | $5,000 | ||||
| Coinsurance | 100% | 100% | 80% | 100% | ||||
| Maximum Out-of-Pocket | ||||||||
| Individual | $12,000 | $12,000 | N/A | $12,000 | ||||
| Family | $24,000 | $24,000 | N/A | $24,000 | ||||
| Physician Office Visit | ||||||||
| Primary Care | $25 copay | $25 copay | 80% after deductible | $25 copay after deductible | ||||
| Specialty Care | $35 copay | $35 copay | 80% after deductible | $25 copay after deductible | ||||
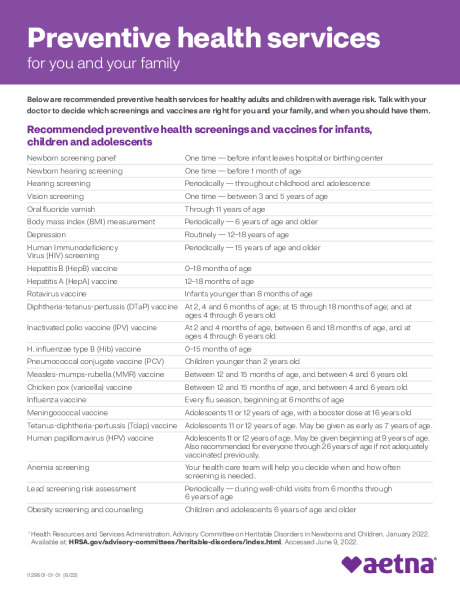
| Preventive Care | ||||||||
| Adult Periodic Exams | 100% | 100% | Not Covered | 100% | ||||
| Well-Child Care | 100% | 100% | Not Covered | 100% | ||||
| Diagnostic Services | ||||||||
| X-ray / Lab Tests | 100% | 100% | 80% after deductible | 100% after deductible | ||||
| Complex Radiology | 100% | 100% | 80% after deductible | 100% after deductible | ||||
| Urgent Care Facility | $25 copay | $25 copay | 80% after deductible | $25 copay after deductible | ||||
| Emergency Room Facility Charges | $100 copay; waived if admitted | $100 copay | $100 copay; waived if admitted | $100 after deductible | ||||
| Inpatient Facility Charges | 100% | 100% | 80% after deductible | 100% after deductible | ||||
| Outpatient Facility and Surgical Charges | 100% | 100% | 80% after deductible | 100% after deductible | ||||
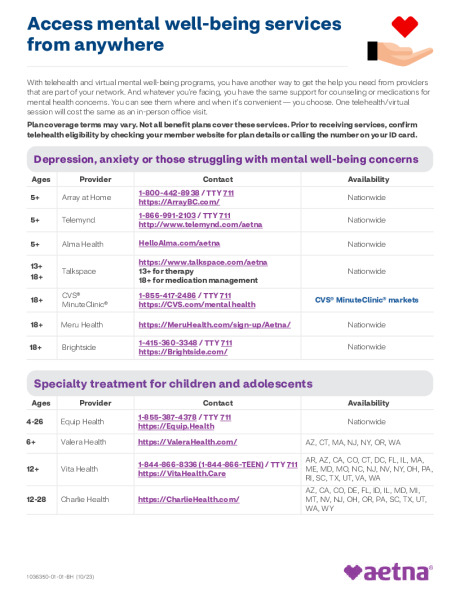
| Mental Health | ||||||||
| Inpatient | 100% | 100% | 80% after deductible | 100% after deductible | ||||
| Outpatient | 100% | 100% | 80% after deductible | 100% after deductible | ||||
| Substance Abuse | ||||||||
| Inpatient | 100% | 100% | 80% after deductible | 100% after deductible | ||||
| Outpatient | 100% | 100% | 80% after deductible | 100% after deductible | ||||
| Other Services | ||||||||
| Chiropractic | 80% after deductible; 30 visits per year | 100% after deductible | ||||||
| Retail Pharmacy (30 Day Supply) | ||||||||
| Generic | $8 copay | $8 copay | Not Covered | $8 copay after deductible | ||||
| Preferred | $30 copay | $30 copay | Not Covered | $30 copay after deductible | ||||
| Non-Preferred | $50 copay | $50 copay | Not Covered | $50 copay after deductible | ||||
| Mail Order Pharmacy (90 Day Supply) | ||||||||
| Generic | $16 copay | $16 copay | Not Covered | $16 copay after deductible | ||||
| Preferred | $60 copay | $30 copay | Not Covered | $60 copay after deductible | ||||
| Non-Preferred | $100 copay | $90 copay | Not Covered | $100 copay after deductible | ||||
Note: Please consult plan documents for full benefits, exclusions, and limitations.