2027
Benefits Info

Retirees under 65 along with their spouse and or dependent children are eligible for the benefits described below.

  • Medical (spouse, and/or children up to age 26)
    • scroll down for medical plan information
  • Dental (spouse and/or children up to age 26)
  • Vision (spouse and/or children up to age 26)

Medical Plan Comparison

New Castle County will continue to offer medical coverage. The below charts are a brief outline of the plan options.

New Castle Offers Plans through Highmark Blue Cross Blue Shield and Aetna.

Highmark BlueCross BlueShield Plans

Under 65

UNDER 65 Highmark Blue Cross Blue Shield
Highmark PPO
Highmark Blue Cross Blue Shield
Highmark EPO
Highmark Blue Cross Blue Shield
Highmark Passive PPO
In-Network
Benefits
Out-of-Network
Benefits
Schedule of Benefits Schedule of Benefits
Annual Deductible
Individual $0 $200 $0 $200
Family $0 $400 $0 $400
Coinsurance 100% 80% 100% 80%
Maximum Out-of-Pocket
Individual $12,000 N/A $12,000 $12,000
Family $24,000 N/A $24,000 $24,000
Physician Office Visit
Primary Care $25 copay 80% after deductible $25 copay 80% after deductible
Specialty Care $35 copay 80% after deductible $35 copay 80% after deductible
Preventive Care
Adult Periodic Exams/ Well Child Care 100% Not covered 100% 100%
Diagnostic Services
X-ray and Lab Tests 100% 80% after deductible 100% 100%
Complex Radiology 100% 80% after deductible 100% 100%
Urgent Care Facility $25 copay 80% after deductible $25 copay 80% after deductible
Emergency Room Facility Charges $100 copay per visit; waived if admitted $100 copay per visit; waived if admitted $100 copay per visit; waived if admitted 100%
Inpatient Facility Charges 100% 80% after deductible 100% 100%
Outpatient Facility and Surgical Charges 100% 80% after deductible 100% 100%
Mental Health
Inpatient 100% 80% after deductible 100% 100%
Outpatient 100% 80% after deductible 100% 80% after deductible
Substance Abuse
Inpatient 100% 80% after deductible 100% 100%
Outpatient 100% 80% after deductible 100% 80% after deductible
Retail Pharmacy (30 Day Supply)
Generic $8 copay Not covered $8 copay 20% after deductible
Preferred $30 copay Not covered $30 copay 20% after deductible
Non-Preferred $50 copay Not covered $50 copay 20% after deductible
Mail Order Pharmacy (90 Day Supply)
Generic $16 copay Not covered $16 copay 20% after deductible
Preferred $60 copay Not covered $60 copay 20% after deductible
Non-Preferred $100 copay Not covered $100 copay 20% after deductible

Note: Please consult plan documents for full benefits, exclusions, and limitations.

Highmark Plan Documents

Medical Plan Summaries - Under 65

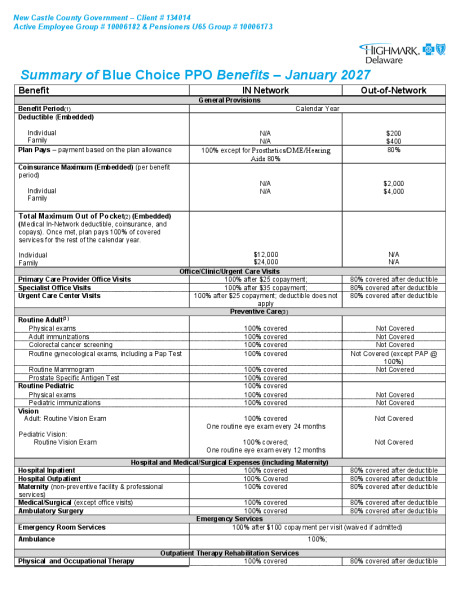
2027 Highmark PPO Plan Summary
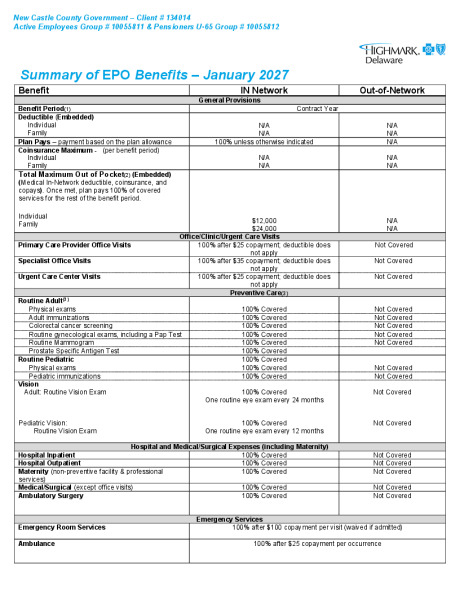
2027 Highmark EPO Plan Summary
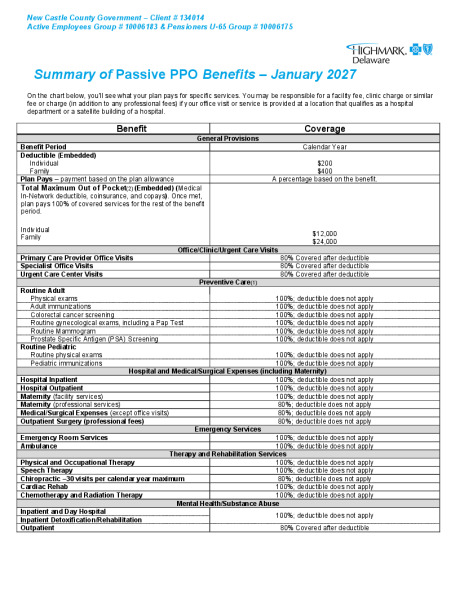
2027 Highmark Passive PPO Plan Sumary (formerly Comp80

Reference - Under 65

2024 High Level Open Enrollment Brochure, DE, MX2455665

Highmark Member Engagement

Highmark Urgent Care

Seasonal Well360 Virtual Health Individual Flyer, DE, MX1722595

Highmark Coaching Program

WELLNESS COACHING - 47 LB. WEIGHT LOSS (1)

Highmark Sword Campaign

Highmark CRM Blue365

My Highmark Intro Flyer, DE, MX2249801 (1)

Diabetes Prevention Program

Video: Diabetes Prevention Program

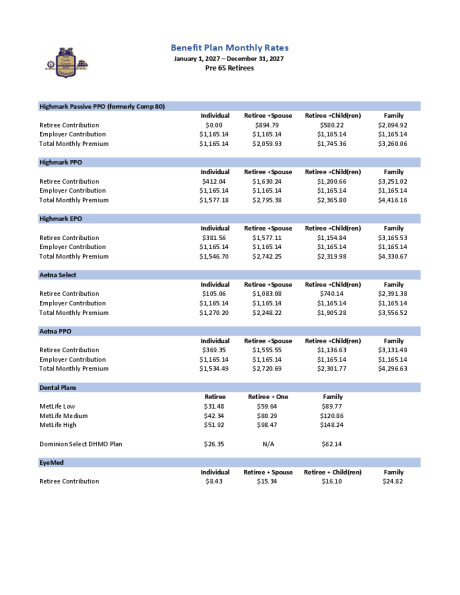
Under 65 - Benefit Plan Monthly Rates

2027 Total Monthly Premium Rates Pre 65 Retirees

Medical Plan Comparison (Under 65)

FULL-TIME & UNDER 65 AetnaOpen Access Select Aetna
Aetna PPO
Aetna Medical QHDHP
HSA Compatible
Schedule of Benefits In-Network Benefits Out-of-Network Benefits Schedule of Benefits
Annual Deductible
Individual $0 $0 $200 $2,500
Family $0 $0 $400 $5,000
Coinsurance 100% 100% 80% 100%
Maximum Out-of-Pocket
Individual $12,000 $12,000 N/A $12,000
Family $24,000 $24,000 N/A $24,000
Physician Office Visit
Primary Care $25 copay $25 copay 80% after deductible $25 copay after deductible
Specialty Care $35 copay $35 copay 80% after deductible $25 copay after deductible
Preventive Care
Adult Periodic Exams 100% 100% Not Covered 100%
Well-Child Care 100% 100% Not Covered 100%
Diagnostic Services
X-ray / Lab Tests 100% 100% 80% after deductible 100% after deductible
Complex Radiology 100% 100% 80% after deductible 100% after deductible
Urgent Care Facility $25 copay $25 copay 80% after deductible $25 copay after deductible
Emergency Room Facility Charges $100 copay; waived if admitted $100 copay $100 copay; waived if admitted $100 after deductible
Inpatient Facility Charges 100% 100% 80% after deductible 100% after deductible
Outpatient Facility and Surgical Charges 100% 100% 80% after deductible 100% after deductible
Mental Health
Inpatient 100% 100% 80% after deductible 100% after deductible
Outpatient 100% 100% 80% after deductible 100% after deductible
Substance Abuse
Inpatient 100% 100% 80% after deductible 100% after deductible
Outpatient 100% 100% 80% after deductible 100% after deductible
Other Services
Chiropractic 80% after deductible; 30 visits per year 100% after deductible
Retail Pharmacy (30 Day Supply)
Generic $8 copay $8 copay Not Covered $8 copay after deductible
Preferred $30 copay $30 copay Not Covered $30 copay after deductible
Non-Preferred $50 copay $50 copay Not Covered $50 copay after deductible
Mail Order Pharmacy (90 Day Supply)
Generic $16 copay $16 copay Not Covered $16 copay after deductible
Preferred $60 copay $30 copay Not Covered $60 copay after deductible
Non-Preferred $100 copay $90 copay Not Covered $100 copay after deductible

Note: Please consult plan documents for full benefits, exclusions, and limitations.

Aetna Plan Documents

Medical Plan Summaries (Under 65)

2027 Aetna Open Access Select Plan Summary
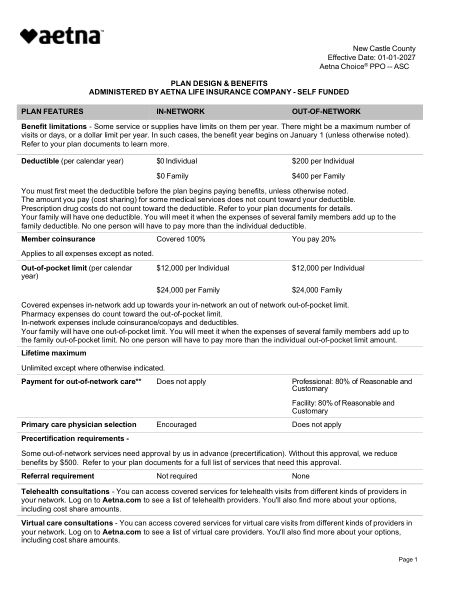
2027 Aetna PPO Plan Summary

2027 Aetna High Deductible Plan Summary
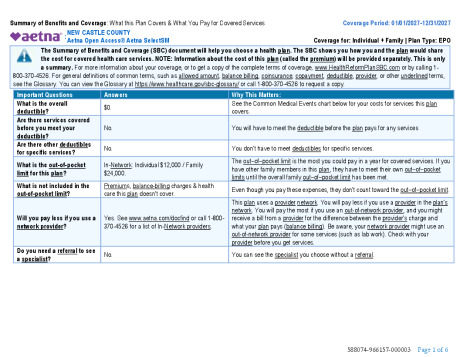
Summary of Benefits and Coverage (Under 65)

2027 Aetna Open Access® Aetna Select SBC
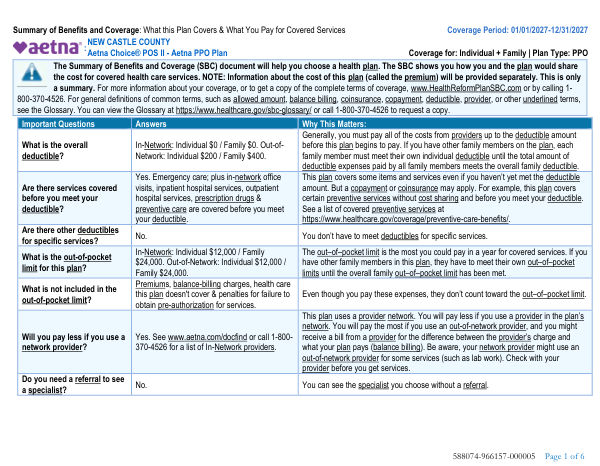
2027 Aetna PPO SBC
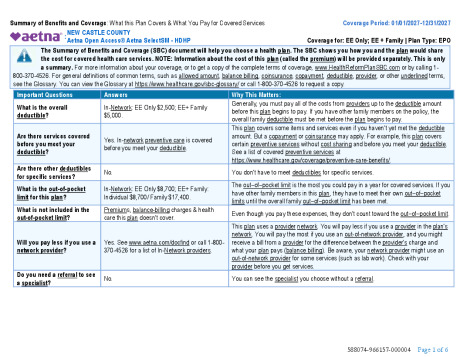
2027 Aetna HDHP SBC

Aetna Resources

24-Hour Nurse Line Member Flyer Post-Enrollment

Aetna Health App
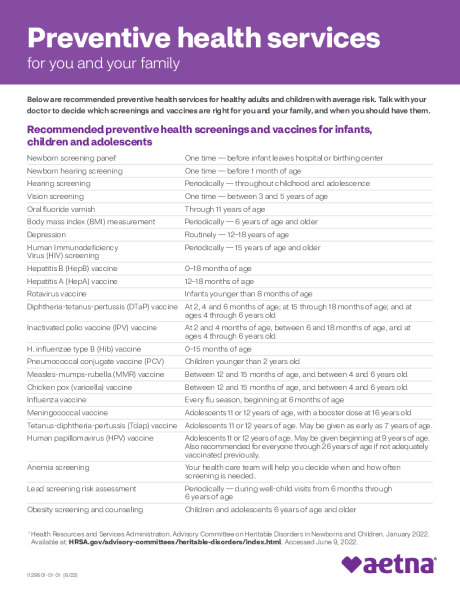
Preventive Care Schedule
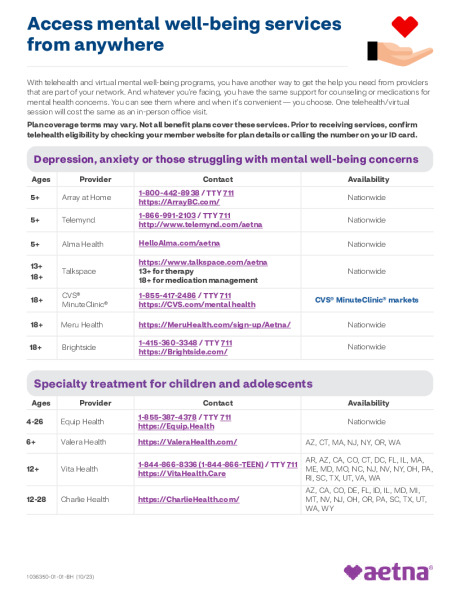
Behavior Health Programs and Services

Achieving a healthy weight

Aetna Hinge Health

LifeMart Discounts Program

Weight Management Discounts

Under 65 - Benefit Plan Monthly Rates

2027 Total Monthly Premium Rates Pre 65 Retirees